
Endometriosis: Symptoms, Diagnosis, and Treatment
Pelvic pain is frequently dismissed as an inconvenient reality of the menstrual cycle. For individuals with endometriosis, however, that discomfort is rarely ordinary cramping. It is often a chronic, debilitating condition that interferes with work, relationships, and everyday physical function.
According to data compiled by the Eunice Kennedy Shriver National Institute of Child Health and Human Development (NICHD), endometriosis affects an estimated 10% of reproductive-age women globally. Despite its prevalence, patients in the United States often endure an average diagnostic delay of seven to ten years from the onset of symptoms. Closing this gap begins with recognizing what endometriosis actually is, understanding why it is so frequently missed, and identifying current evidence-based pathways for relief.

Table of Contents
What Endometriosis Is (and What It Is Not)
To understand endometriosis, it helps to start with the endometrium—the specialized tissue lining the inside of the uterus that thickens and sheds each month during menstruation.
In endometriosis, tissue that is similar to (though biologically distinct from) the uterine lining implants and grows outside the uterine cavity. These lesions most commonly attach to the ovaries, fallopian tubes, outer uterine surface, uterosacral ligaments, and the pelvic peritoneum. In more extensive presentations, lesions may involve the bladder, ureters, intestines, or rectovaginal septum.
Just like the normal uterine lining, these ectopic implants respond to cyclic hormonal fluctuations: they swell, break down, and bleed with every menstrual cycle. Because this blood and shed tissue have no anatomical exit from the pelvic cavity, they trigger localized inflammation, nerve irritation, immune cell recruitment, and progressive fibrosis. Over time, this recurring cycle can lead to dense bands of scar tissue (adhesions) that fuse adjacent organs together, causing structural distortion and chronic pain.
Recognizing the Symptoms
Endometriosis symptoms vary widely in severity, and a person’s pain level does not always correlate with the anatomical extent of their lesions. Someone with superficial, early-stage implants may experience severe pain, while an individual with extensive pelvic adhesions may have minimal discomfort.
Common clinical presentations include:
- Severe dysmenorrhea (painful periods): Menstrual cramps that fail to respond adequately to standard doses of over-the-counter NSAIDs, often radiating into the lower back, pelvis, and upper thighs.
- Deep dyspareunia: Pain during or after sexual intercourse, typically described as a sharp, deep pelvic ache rather than superficial discomfort.
- Chronic non-menstrual pelvic pain: Persistent aching, pressure, or fullness in the pelvis that occurs outside the menstrual window.
- Gastrointestinal and urinary distress: Painful bowel movements (dyschezia), cyclical diarrhea or constipation, painful urination (dysuria), or bladder spasms, frequently worsening during menses.
- Subfertility or infertility: Difficulty conceiving, often prompting the first formal medical investigation in otherwise asymptomatic individuals.
- Systemic fatigue: Profound, persistent exhaustion driven by chronic inflammatory activation.
Because symptoms like bloating, constipation, and pelvic cramping overlap with conditions such as irritable bowel syndrome (IBS), pelvic inflammatory disease, and interstitial cystitis, endometriosis is frequently misattributed to digestive or non-gynecologic causes.
The Modern Diagnostic Pathway
Historically, the medical standard held that endometriosis could only be confirmed via invasive exploratory surgery. Today, clinical practice guidelines have shifted toward a structured, multi-step clinical approach that prioritizes earlier intervention.
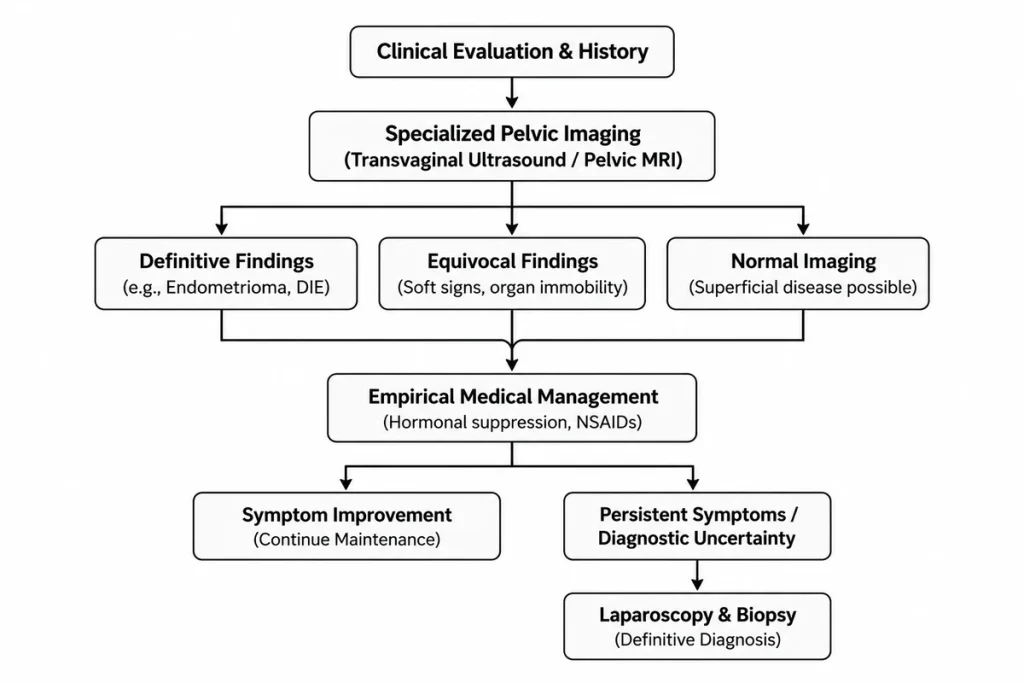
1. Clinical Suspicion and Empirical Therapy
Current clinical guidelines from the American College of Obstetricians and Gynecologists (ACOG) support initiating empirical therapy based on strong clinical suspicion without requiring immediate surgery. If an adolescent or adult presents with classic pelvic pain that disrupts daily activities, clinicians can reasonably begin first-line medical therapy to evaluate symptom response.
2. High-Resolution Imaging
Standard abdominal ultrasound is rarely sufficient to identify endometriosis. However, specialized imaging performed by experienced practitioners has become increasingly valuable:
- Advanced Transvaginal Ultrasound (TVUS): Can reliably identify endometriomas (ovarian cysts filled with old hemolyzed blood, often called “chocolate cysts”) and assess “sliding sign” organ mobility to detect deep infiltrating endometriosis (DIE) of the bowel or bladder.
- Pelvic Magnetic Resonance Imaging (MRI): Useful for mapping the depth and extent of infiltrating nodules and evaluating pelvic anatomy prior to planned surgical procedures.
Normal imaging does not rule out endometriosis. Early, superficial peritoneal lesions are typically invisible on ultrasound and MRI.
3. Diagnostic Laparoscopy
Minimally invasive laparoscopy remains the gold standard for definitive confirmation. A surgeon inserts a thin camera through a small umbilical incision to inspect the pelvic and abdominal cavities directly. Biopsies of suspicious areas are excised and sent to pathology for histologic confirmation of endometrial-like glands and stroma.
Evidence-Based Treatment Options
There is currently no permanent cure for endometriosis. Treatment focuses on reducing chronic pelvic pain, suppressing lesion proliferation, preserving or restoring fertility, and optimizing daily quality of life.
Pharmacological Approaches
Medical therapy is primarily aimed at interrupting the hormonal cycles that stimulate lesion activity:
| Medication Class | Mechanism of Action | Common Examples | Considerations & Limitations |
| Combined Hormonal Contraceptives | Suppress ovulation and thin endometrial tissue | Low-dose oral pills, transdermal patches, vaginal rings | Often taken continuously to eliminate menstrual bleeding; first-line therapy |
| Progestin-Only Therapies | Inhibit estrogen-driven proliferation; induce atrophy | Norethindrone, medroxyprogesterone, levonorgestrel-releasing IUD | Highly effective for pain; irregular spotting is common in early months |
| GnRH Antagonists | Dose-dependently suppress pituitary gonadotropin release | Elagolix, relugolix (often paired with add-back hormone therapy) | Rapid pain relief; requires monitoring for bone mineral density loss and vasomotor signs |
| Nonsteroidal Anti-Inflammatory Drugs | Inhibit prostaglandin synthesis to reduce inflammation | Ibuprofen, naproxen | Targets pain pathways; does not shrink lesions or prevent disease progression |
For many individuals managing severe inflammatory pain flares, over-the-counter pain medications provide baseline relief. However, relying heavily on oral pain relievers requires careful attention to the safe use and limits of ibuprofen to protect stomach lining and kidney function over time.
Surgical Intervention
When medical therapies fail, are contraindicated, or when fertility is an immediate priority, surgical intervention is considered:
- Conservative Laparoscopic Excision: The surgical removal of visible lesions down to healthy margins. Excision is widely preferred over superficial ablation (burning/cautery), as it provides tissue for histologic review and is associated with lower recurrence rates for deep lesions.
- Ovarian Cystectomy: Careful stripping of endometrioma capsules while sparing as much healthy ovarian reserve as possible.
- Hysterectomy and Oophorectomy: Historically viewed as a definitive solution, removing the uterus and ovaries is now considered a final option reserved for severe, intractable pain or coexisting adenomyosis. Even after a hysterectomy, peritoneal lesions left behind can continue to cause pain if stimulated by residual or exogenous hormones.
Multidisciplinary Supportive Care
Because prolonged pelvic pain frequently induces secondary musculoskeletal and neurological dysfunction, comprehensive care often extends beyond medications and surgery:
- Pelvic Floor Physical Therapy: Chronic guarding against pain routinely causes high-tone pelvic floor dysfunction (hypertonicity). Specialized physical therapy helps relax contracted muscles, easing both deep intercourse pain and urinary urgency.
- Neuropathic Pain Management: In cases where central sensitization has developed, medications targeting nerve signaling (such as gabapentin or tricyclic antidepressants) may be used alongside standard therapies.
When to Seek Specialized Care
Pelvic pain that requires missing school or work, leaves you unable to complete daily routines, or worsens progressively despite over-the-counter medication warrants a comprehensive medical evaluation.
If your symptoms are repeatedly dismissed as standard menstrual cramps, seeking a consultation with a board-certified gynecologist—particularly one experienced in minimally invasive gynecologic surgery (MIGS) or chronic pelvic pain—is an essential next step toward receiving an accurate diagnosis and an individualized treatment plan.











